Anasarca refers to a generalized and massive edema affecting the entire body, from the lower limbs to the face, sometimes extending to the pleural and abdominal cavities. It is not an autonomous disease but a signal of an underlying organ failure, most often cardiac, renal, or hepatic. Understanding the mechanisms that lead to this fluid accumulation helps guide diagnosis and tailor management.
Exudative enteropathy and anasarca: an underestimated digestive cause
Medical articles dedicated to anasarca in adults focus almost exclusively on the trio of heart failure, nephrotic syndrome, and hepatic cirrhosis. Digestive causes are rarely mentioned, even though they can explain cases of massive edema resistant to standard treatments.
Exudative enteropathies cause protein leakage through the intestinal mucosa. Plasma albumin levels drop, oncotic pressure decreases, and fluid migrates into the interstitial tissues. A case published in 2026 describes jejunal tuberculosis presenting as exudative enteropathy with anasarca in an adult, with significant improvement after antituberculous treatment and re-nutrition.
This type of presentation reminds us that in the case of unexplained anasarca, especially if cardiac, renal, and hepatic evaluations return normal, digestive causes of protein loss should be considered. Inflammatory bowel diseases, chronic intestinal infections, and certain lymphangiectasias can produce the same mechanism. To explore resources related to adult anasarca on the Santé Market website, several fact sheets detail complementary diagnostic approaches.
Mechanism of generalized edema formation in adults
Anasarca results from an imbalance between hydrostatic pressure (which pushes fluid out of the vessels) and oncotic pressure (which retains it inside). Three main mechanisms, sometimes combined, explain this disruption of balance.
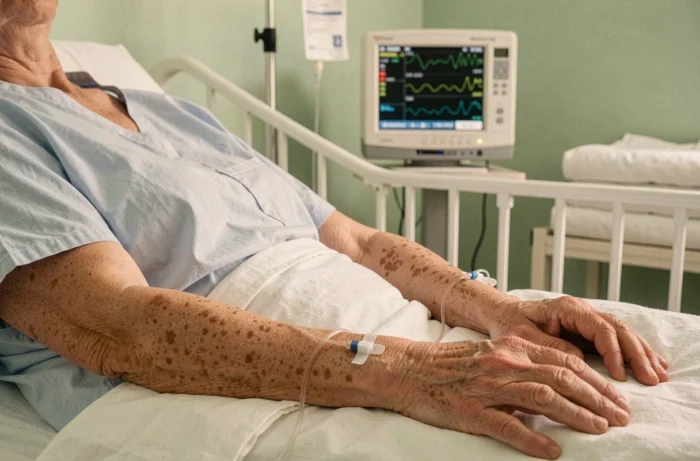
- Hydrosodic overload: heart failure reduces renal filtration rate, leading to water and sodium retention. Fluid first accumulates in the lower limbs and then generalizes if the failure progresses.
- Drop in plasma albumin: nephrotic syndrome (urinary protein leakage), cirrhosis (hepatic synthesis defect), and exudative enteropathies (digestive leakage) decrease oncotic pressure. Fluid leaves the vessels without sufficient pulling force.
- Increased capillary permeability: certain severe inflammatory states, such as sepsis or severe drug reactions, alter the endothelial barrier. Fluid and proteins pass freely into the tissues.
In clinical practice, these mechanisms often coexist. A cirrhotic patient may have a combination of hypoalbuminemia, portal hypertension, and secondary renal sodium retention.
Symptoms of anasarca and warning signs
The generalized swelling of the body is the most visible sign. The skin becomes tight, shiny, and sometimes translucent in the lower limbs. A rapid weight gain over a few days is a major warning sign, as it indicates significant fluid retention rather than an increase in fat mass.
Anasarca is not limited to subcutaneous tissues. Fluid can accumulate in the abdominal cavity (ascites), around the lungs (pleural effusion), or around the heart (pericardial effusion). These internal effusions worsen the situation by compressing the organs.
Dyspnea occurs when fluid reaches the lungs or pleura. The patient experiences difficulty breathing first during exertion and then at rest in advanced forms. A decrease in urinary volume associated with increasing edema points towards renal impairment or decompensated heart failure.
Treatments for anasarca: diuretics and addressing the cause
The treatment of anasarca relies on two simultaneous axes: reducing fluid overload and treating the underlying pathology.
Diuretics and sodium restriction
Loop diuretics remain the first-line symptomatic treatment. They increase renal excretion of sodium and water. In the case of insufficient response, recent recommendations from the European Society of Cardiology (2025 guidelines) advocate for a staged diuretic strategy with reassessment every six hours for congestion related to heart failure. The goal is to adjust doses based on measured urinary response.
Restricting salt intake complements the action of diuretics. In patients with heart failure, this hygienic-dietary measure is still recommended despite diverging data on the appropriate level of restriction.
Etiological treatment
Treating anasarca without correcting the underlying cause yields only temporary results. In the case of nephrotic syndrome, controlling proteinuria with immunosuppressive or nephroprotective treatments is crucial for resolving edema. For decompensated cirrhosis, paracentesis combined with albumin infusion relieves overload, but liver transplantation remains the only sustainable option in some cases.
In cases of exudative enteropathies, re-nutrition and treatment of the intestinal disease (such as antituberculous antibiotic therapy) can gradually restore albumin levels and resolve edema.
New mineralocorticoid receptor antagonists and cardiac anasarca
Recent European guidelines include finerenone, a non-steroidal mineralocorticoid receptor antagonist, in the management of heart failure associated with chronic kidney disease. This molecule, initially developed for diabetic nephropathy, shows a tolerance profile distinct from classic steroid antagonists like spironolactone, with a lower risk of severe hyperkalemia.
For patients with anasarca on a combined cardiac and renal background, this advancement opens an additional therapeutic option. The available data do not yet allow for conclusions about the specific impact of finerenone on the resolution of massive edema, but its inclusion in the recommendations reflects an evolution in the management of congestion.
Anasarca in adults remains a clinical sign that requires methodical exploration beyond the most common causes. Intestinal tuberculosis, exudative enteropathies, and combined cardio-renal impairments remind us that the differential diagnosis must remain broad. Treatment always relies on correcting the cause, as diuretics alone are insufficient to sustainably resolve an imbalance whose origin lies elsewhere.


